
Introduction
Catheter-associated urinary tract infections are among the most common healthcare-associated infections. They are also among the most preventable. Because nurses place, maintain, and often remove urinary catheters, nursing practice drives CAUTI rates more than almost any other factor. This guide covers the evidence-based bundle, the role of nurse-driven removal, and the daily habits that keep patients safe.
Table of Contents
- What Is CAUTI?
- Why CAUTI Matters
- The Prevention Principle: Avoid and Remove
- Appropriate Indications
- Alternatives to an Indwelling Catheter
- The Insertion Bundle
- The Maintenance Bundle
- Nurse-Driven Removal
- Post-Removal Care
- Surveillance and Diagnosis
- Complications
- NCLEX Tips and Memory Tricks
- Clinical Pearls
- Key Takeaways
- FAQs
- References
What Is CAUTI?
A catheter-associated urinary tract infection (CAUTI) is a urinary tract infection in a patient with an indwelling urinary catheter. For surveillance, the CDC’s NHSN requires that the catheter has been in place for more than two consecutive days, and that the patient shows at least one qualifying sign, such as fever above 38.0°C. Importantly, symptoms like frequency, urgency, and dysuria can’t count when a catheter is in place, because the catheter itself can cause them.
Why CAUTI Matters
CAUTIs cause patient discomfort, longer hospital stays, higher costs, and higher mortality. Reports estimate that more than 13,000 deaths each year are associated with UTIs. Because catheters give bacteria a direct path into the bladder, every catheter day adds risk. Therefore, prevention focuses on catheter use and duration first.
The Prevention Principle: Avoid and Remove
Prevention programs aim to do two things: reduce unnecessary catheter placement, and shorten the time a catheter stays in. Nothing else matters as much. In the ANA’s words, catheters should be used only when absolutely necessary and removed as soon as possible. As a result, the first question at every encounter is simple: “Does this patient still need this catheter?”
Appropriate Indications
Common appropriate reasons include:
- Acute urinary retention or bladder outlet obstruction
- Accurate hourly output measurement in critically ill patients
- Perioperative use for selected surgeries
- Healing of stage 3 or 4 sacral or perineal pressure injuries in incontinent patients
- Prolonged immobilization, such as an unstable spine or pelvic fracture
- Comfort at the end of life when needed
Inappropriate reasons include:
- Managing incontinence in a patient who can use other methods
- Staff convenience
- Obtaining a urine culture from a patient who can void
- Prolonged postoperative use without a clear indication
CDC guidance recommends removing the catheter as soon as possible after surgery, preferably within 24 hours, unless a clear reason exists to keep it.
Alternatives to an Indwelling Catheter
- External catheters for patients without retention or obstruction
- Intermittent straight catheterization for patients who need bladder emptying
- Bladder scanners to confirm retention before inserting a catheter
- Scheduled toileting and prompted voiding
- Absorbent products and skin care for incontinence
The Insertion Bundle
- Confirm that the order and the clinical indication match
- Perform hand hygiene before and after the procedure
- Use trained personnel
- Use sterile gloves, drape, sponges, and antiseptic solution
- Maintain aseptic technique throughout
- Choose the smallest catheter that drains well
- Secure the catheter after insertion
- Document the indication, date, and time
The Maintenance Bundle
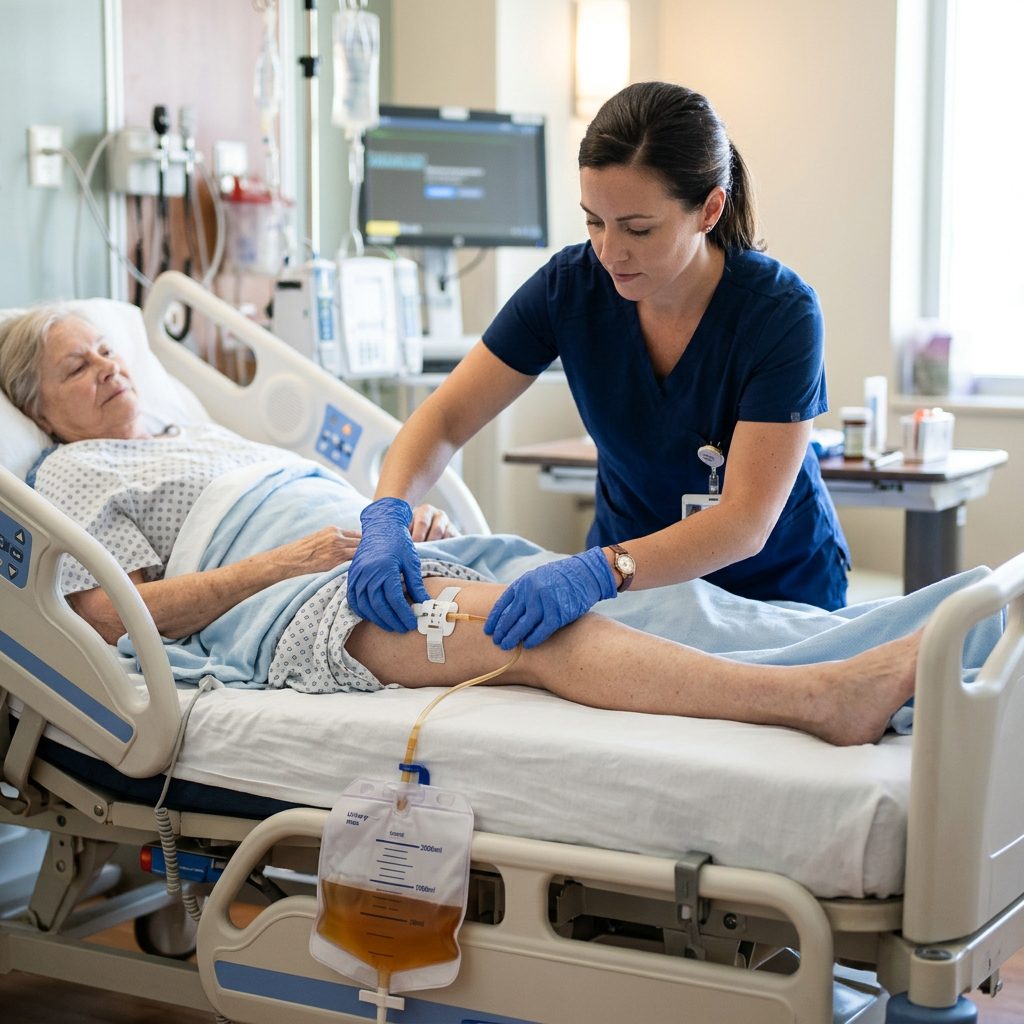
- Secure the catheter to the thigh or abdomen to prevent traction and urethral trauma
- Keep the drainage system closed. Don’t disconnect the catheter from the tubing unless medically necessary
- Keep the bag below bladder level and off the floor at all times
- Avoid dependent loops and kinks in the tubing
- Empty the bag regularly using a clean, separate container for each patient, and avoid touching the spout
- Perform routine hygiene of the meatal area with soap and water during daily bathing
- Avoid routine irrigation unless obstruction is expected
- Collect specimens from the sampling port using aseptic technique
- Don’t change catheters on a fixed schedule, only when clinically needed
Nurse-Driven Removal
Nurse-driven removal protocols give nurses authority to remove a catheter when it no longer meets approved criteria. In a review of 30 studies, daily criteria review, reminders, stop orders, and nurse-empowered removal protocols reduced CAUTI by 53%. A separate bundle study found that CAUTI dropped from 5.4 to 1.41 per 1,000 catheter days after a nurse-empowered, all-or-none bundle. Bundle compliance also rose from 56% to 93%.
Practical tools include:
- A daily catheter necessity checklist
- Chart or bag reminders
- Automatic stop orders, such as removal on postoperative day 1 or 2
- Bladder scan protocols after removal
Post-Removal Care
- Watch for the first void, commonly within about 6 to 8 hours
- Use a bladder scan protocol if the patient doesn’t void
- Encourage fluids, mobility, and toileting
- Re-catheterize only when criteria apply, preferably with intermittent catheterization
- Monitor for fever, dysuria, flank pain, and new confusion
Surveillance and Diagnosis
- Don’t send urine cultures without symptoms
- Don’t treat asymptomatic bacteriuria in most patients
- Collect cultures from a freshly placed catheter or the sampling port when infection is suspected
- Report catheter days and CAUTI events to the unit’s infection prevention team
- Review unit CAUTI rates often, since feedback helps drive improvement
Complications
- Symptomatic UTI and pyelonephritis
- Bloodstream infection and sepsis
- Urethral trauma and strictures
- Bladder spasms and discomfort
- Longer hospital stay
- Death, in severe cases
NCLEX Tips and Memory Tricks
- The best prevention is not placing the catheter, or removing it early.
- Keep the bag below the bladder and off the floor.
- Keep the system closed.
- Don’t irrigate or change catheters routinely.
- Don’t culture or treat urine without symptoms.
- Mnemonic — “CATHETER”: Check indication daily, Aseptic insertion, Tube secured, Hygiene daily, Empty the bag properly, Track catheter days, Early removal, Review with the team.
Clinical Pearls
- Ask “why is this catheter still here?” every shift. Habit, not need, keeps many catheters in.
- A bladder scan before catheterizing often shows that the patient doesn’t need one.
- Don’t let a new fever in a catheterized patient default to “UTI.” Look for other sources first, then use symptoms and cultures wisely.
Key Takeaways
- CAUTI prevention starts with avoiding unnecessary catheters and removing them promptly.
- Insertion and maintenance bundles protect patients through aseptic technique, securement, a closed system, and proper bag position.
- Nurse-driven removal protocols and reminders cut CAUTI substantially.
- Surveillance and stewardship, including avoiding needless cultures, support long-term success.
FAQs
What are the appropriate indications for an indwelling urinary catheter?
Acute retention or obstruction, hourly output monitoring in critical illness, selected perioperative needs, healing of severe sacral or perineal pressure injuries in incontinent patients, prolonged immobilization, and end-of-life comfort.
How do nurses prevent CAUTI?
They avoid unnecessary catheters, follow insertion and maintenance bundles, review catheter need daily, and remove catheters promptly when criteria no longer apply.
What is a nurse-driven catheter removal protocol?
A protocol that lets nurses remove a catheter when it no longer meets approved clinical indications, without waiting for a new order each time.
How should a urinary drainage bag be positioned?
Below bladder level, off the floor, with no kinks or dependent loops in the tubing.
What alternatives exist to an indwelling urinary catheter?
External catheters, intermittent straight catheterization, bladder scanning, scheduled toileting, and absorbent products with good skin care.
References
- CDC — Guideline for Prevention of Catheter-Associated Urinary Tract Infections
- CDC STRIVE — Appropriate Use and Prompt Removal of Indwelling Urinary Catheters
- APIC — Guide to Preventing Catheter-Associated Urinary Tract Infections (2025)
- SAGE Open Nursing (2025) — Assessing the Impact of a Preventive Care Bundle and Nursing Empowerment on CAUTI Rates
- American Nurses Association — CAUTI Prevention Tool
RELATED ARTICLES :
- https://rn-nurse.com/central-line-care/
- https://rn-nurse.com/proper-hand-hygiene-prevent-infections/
- https://rn-nurse.com/standard-vs-transmission-based-precautions/
- https://rn-nurse.com/infection-control-standard-vs-transmission-based-precautions-nclex-nursing-guide/
- https://rn-nurse.com/sepsis-management/
- https://rn-nurse.com/fall-precautions-nursing/